

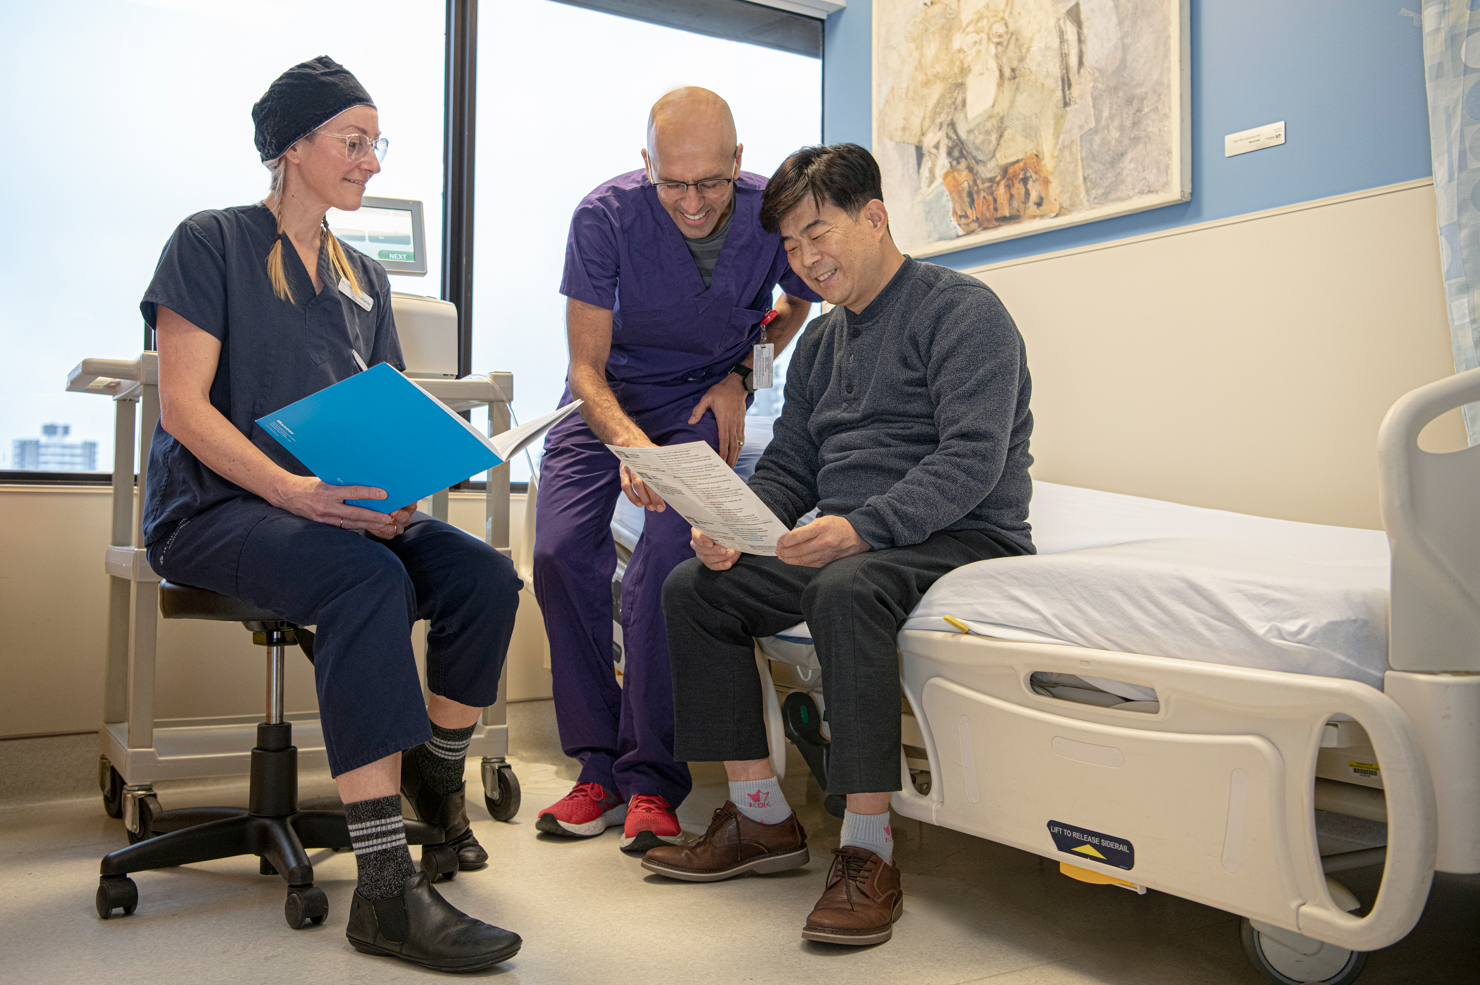

In recent weeks, we invited readers and health-care professionals to share stories about why Catholic health care matters. The response was thoughtful and deeply personal. The following reflection from a longtime nurse practitioner at St. Paul’s Hospital in Vancouver offers a firsthand account of how faith shapes care in daily practice.
I have been a nurse practitioner at St. Paul’s Hospital since 2006. Over the years, I have had many opportunities to leave for other health authorities, yet I have made a deliberate choice to remain at Providence Health Care. What has kept me here is not convenience or habit, but a deep personal conviction and sense of vocation rooted in our mission: “Inspired by the healing ministry of Jesus Christ, Providence Health Care is a Catholic health care community dedicated to meeting the physical, emotional, social, and spiritual needs of those served through compassionate care, teaching, and research.”
That mission is not abstract. I have seen it lived out in quiet, ordinary, deeply human moments—moments that felt unmistakably different because they occurred within a Catholic health care setting.
Meeting patients where they are
While working in the heart failure clinic, I cared for a man who was recently widowed, living alone, and approaching the end of life with advanced heart failure. Simply getting to the hospital for outpatient appointments was overwhelming for him. Even walking from the HandyDART drop-off to the fifth-floor clinic caused significant physical distress.
At that time, our clinic was not structured to offer home visits. Yet when I requested them, the clerical team moved quickly and creatively to make it possible. I visited him at home several times.
Yes, his symptoms were better managed. His physical suffering was eased. But what remains with me most vividly are the conversations—about his wife, whom he dearly loved and had recently lost, and about his passion for cooking for her. He was profoundly lonely, and that loneliness caused a suffering no medication could address. Those visits offered companionship, dignity, and presence. They alleviated his isolation and accompanied him through to his natural death.
Being seen and heard
Another patient in the heart failure clinic, also nearing the end of life, attended visits with his wife. His cardiac symptoms were reasonably controlled, but his most distressing complaint was something seemingly small: a severely painful ingrown toenail.
Once again, our clerical team helped arrange a home visit, which was not a standard option. I could not treat the toenail myself, but I took his concern seriously and referred him directly to a compassionate podiatrist in the community who also practised at St. Paul’s Hospital. He died a few months later.
Eight years after his death, his wife went out of her way to find me working in the atrial fibrillation clinic. She simply wanted to tell me how much that visit had meant to both of them. His pain had been relieved, but more importantly, she said, he felt seen, heard, and validated. That mattered most to him at the end of his life.
Choosing presence over despair
Another patient, in his early 60s, was under my care in the atrial fibrillation clinic. He lived alone, worked from home, and struggled with anxiety about medications. Over time, uncontrolled atrial fibrillation led to heart failure.
Although he experienced palpitations and shortness of breath, his greatest source of suffering was something many clinicians dismissed: severe, constant phlegm in his throat. He described it as crippling and deeply embarrassing. He felt unheard by the health system and had never been given a clear explanation or appropriate referrals.
Acknowledging his frustration, I followed him closely through telemedicine, referring him to specialists and checking in regularly. He was isolated, depressed, and increasingly hopeless. Eventually, he told me he intended to pursue medical assistance in dying—not because of his heart disease, but because of the despair caused by unresolved suffering and isolation.
He was approved for MAiD in the community. He had two scheduled dates, which he cancelled. He told me he did not want MAiD, but felt he had no other option.
A few days before Christmas 2023, I had a strong sense that I needed to check in. When I called, he was acutely short of breath and in critical heart failure. That day, instead of going to a community location for his scheduled death through MAiD, he chose to present to the emergency department at St. Paul’s Hospital—knowing MAiD would not be available there.
I met him in person for the first time in the emergency room. He thanked me for listening, advocating, and accompanying him through our many virtual visits. He died peacefully on Christmas Eve. His ex-wife was able to be with him.
Through my vocation as a nurse practitioner, I feel called to listen more deeply, accompany more patiently, and remain non-judgmental, seeing every person first and always as a child of God, loved by God. Catholic health care has formed me to advocate quietly but clearly for relational, holistic care that honours the dignity of the person in front of me and supports families without fear.
Catholic health care does not deny suffering. It acknowledges it, names it, and stays with it. It also insists that suffering is not meaningless. Despair arises when suffering is stripped of meaning and relationship.
The outcome we hope for is not division, but healing; not fear, but trust; not abandonment, but accompaniment. Catholic health care bears witness to the truth that no one should suffer alone, and that compassionate presence, rooted in love and dignity, restores hope when a physical cure is no longer possible.
Belinda-Ann Furlan, NP(F), MScN, is head of the Providence Health Care department of nurse practitioners and a nurse practitioner in the atrial fibrillation clinic at St. Paul’s Hospital. She also serves as an adjunct professor in the UBC school of nursing.
Your voice matters! Join the conversation by submitting a Letter to the Editor here.







